

Semaglutide has dominated the medical weight loss landscape since its approval for chronic weight management in 2021. With semaglutide therapy now widely available, a newer contender called retatrutide has emerged from clinical trials with results that redefine what is possible with anti-obesity medications: 24.2% average weight loss at 48 weeks in Phase 2 and 28.3% at 80 weeks in Phase 3, on the 12 mg dose. Both medications work through incretin hormone pathways, but their mechanisms, clinical results, and availability differ substantially.
This comprehensive comparison examines how retatrutide and semaglutide stack up across every dimension that matters: mechanism of action, weight loss results, side effects, availability, cost considerations, and who each medication is best suited for.
Understanding the Fundamentals
What Is Semaglutide?
Semaglutide is a GLP-1 (glucagon-like peptide-1) receptor agonist developed by Novo Nordisk. It mimics the natural GLP-1 hormone, which is released from the gut after eating and plays a central role in appetite regulation and blood sugar control.
Semaglutide is available under several brand names:
- Ozempic: Approved for type 2 diabetes (doses up to 2 mg weekly)
- Wegovy: Approved for chronic weight management (doses up to 2.4 mg weekly)
- Rybelsus: Oral tablet form approved for type 2 diabetes
Semaglutide has the most extensive clinical evidence of any GLP-1 medication for weight loss, with the STEP trial program providing robust data across multiple patient populations. The SELECT cardiovascular outcomes trial further demonstrated a 20% reduction in major adverse cardiovascular events in overweight and obese adults (Lincoff et al., 2023).
What Is Retatrutide?
Retatrutide (development name LY3437943) is an investigational medication developed by Eli Lilly and Company. It represents a new class of drugs: triple hormone receptor agonists. Unlike semaglutide, which targets a single receptor, retatrutide simultaneously activates three metabolic pathways.
The Phase 2 results published in The New England Journal of Medicine generated enormous interest (Jastreboff et al., 2023), and Eli Lilly has since reported five Phase 3 trials. Retatrutide is not yet FDA-approved; Lilly plans to submit it for U.S. approval in the first quarter of 2027.
How They Work: Mechanism of Action
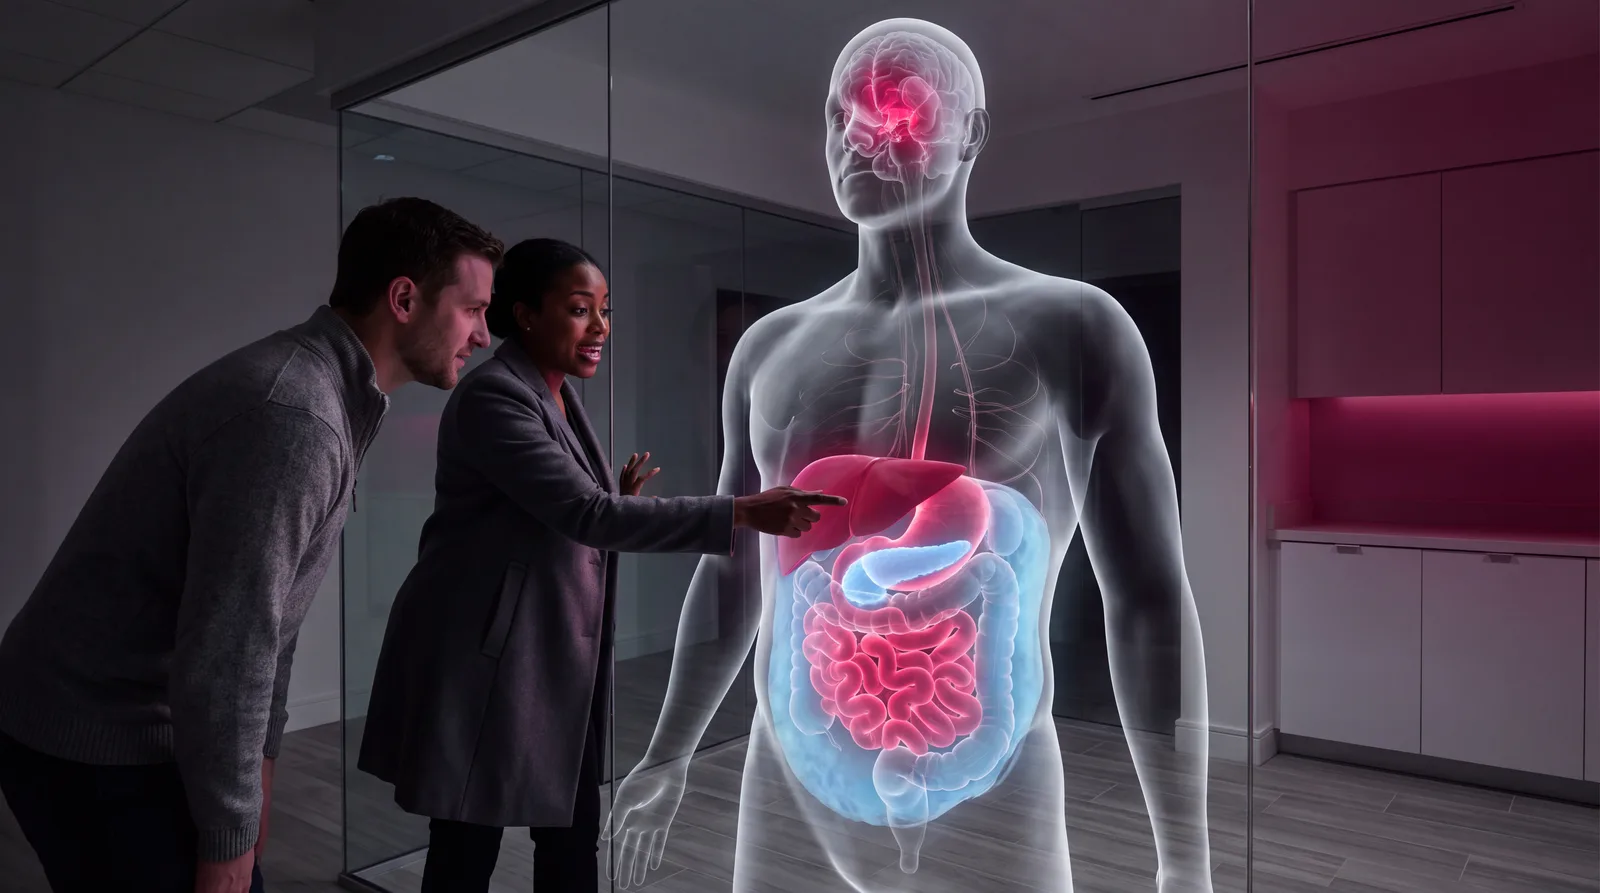
The fundamental difference between these medications lies in how many metabolic pathways they engage.
Semaglutide: Single-Receptor Approach
Semaglutide activates the GLP-1 receptor, producing the following effects:
- Appetite suppression through direct action on hypothalamic neurons that control hunger signaling
- Delayed gastric emptying that promotes prolonged feelings of fullness after meals
- Enhanced glucose-dependent insulin secretion from pancreatic beta cells
- Reduced glucagon secretion (different from glucagon receptor activation) that lowers hepatic glucose output
- Potential neuroprotective effects currently being studied in Alzheimer’s disease trials
Research by Blundell et al. (2017) published in Diabetes, Obesity and Metabolism demonstrated that semaglutide specifically reduces appetite, food cravings, and the desire to eat energy-dense foods through central nervous system mechanisms.
Retatrutide: Triple-Receptor Approach
Retatrutide activates all three of the following receptors simultaneously:
GLP-1 Receptor (shared with semaglutide):
- Appetite suppression and delayed gastric emptying
- Improved insulin secretion and blood sugar regulation
GIP Receptor (shared with tirzepatide):
- Enhanced insulin sensitivity in adipose tissue
- Improved lipid metabolism and nutrient partitioning
- Potential direct effects on fat cell biology that promote fat mobilization
- Research in Cell Metabolism has shown GIP signaling plays critical roles in adipose tissue function (Campbell & Drucker, 2015)
Glucagon Receptor (unique to retatrutide):
- Enhanced hepatic fat oxidation promoting the breakdown of stored fat in the liver
- Lipolysis stimulation that mobilizes fatty acids from adipose tissue
- Added calorie burn in animal studies — in obese mice, the glucagon arm increased energy expenditure on top of reduced food intake (Coskun et al., Cell Metabolism, 2022)
The glucagon receptor component is what truly distinguishes retatrutide. While semaglutide works primarily by reducing how much you eat, retatrutide adds a pathway aimed at stored fat itself — most clearly in the liver, where fat fell 82.4% in 24 weeks on 12 mg in a Phase 2 MRI substudy (Sanyal et al., 2024).
Weight Loss Results: Trial by Trial
Semaglutide Clinical Trial Results
The STEP (Semaglutide Treatment Effect in People with Obesity) trial program is the most comprehensive dataset for any anti-obesity medication:
STEP 1 (Wilding et al., 2021, NEJM):
- 1,961 adults with obesity (BMI 30+) or overweight (BMI 27+) with comorbidities
- Semaglutide 2.4 mg weekly vs. placebo
- Average weight loss: 14.9% over 68 weeks (vs. 2.4% placebo)
- 86.4% of participants lost at least 5% of body weight
- 69.1% lost at least 10%
- 50.5% lost at least 15%
STEP 3 (Wadden et al., 2021, JAMA):
- Combined with intensive behavioral therapy
- Average weight loss: 16.0% over 68 weeks
- Demonstrated that lifestyle support amplifies medication effects
STEP 5 (Garvey et al., 2022, Nature Medicine):
- Two-year duration study
- Average weight loss: 15.2% maintained over 104 weeks
- Demonstrated sustained effectiveness with continued use
Retatrutide Clinical Trial Results
Phase 2 Trial (Jastreboff et al., 2023, NEJM):
- 338 adults with obesity (BMI 30+) or overweight (BMI 27+) with comorbidities
- Multiple dose groups (1 mg, 4 mg, 8 mg, 12 mg weekly)
- Results at the 12 mg dose:
- Average weight loss: 24.2% in 48 weeks
- 100% of participants lost at least 5% of body weight
- 93% lost at least 10%
- 83% lost at least 15%
Phase 3 TRIUMPH-1 (Eli Lilly, May 2026):
- 2,339 adults with obesity or overweight and no diabetes
- Maintenance doses of 4 mg, 9 mg and 12 mg weekly vs. placebo
- Average weight loss: 28.3% on 12 mg over 80 weeks (vs. 2.2% placebo); 25.9% on 9 mg; 19.0% on 4 mg
- 45.3% of the 12 mg group lost at least 30% of body weight
- Counting every participant randomized, adherent or not, the 12 mg result was 25.0%
These are separate trials in different populations and lengths; the two medications have not been compared head to head.
Comprehensive Comparison Table
| Feature | Semaglutide (Wegovy) | Retatrutide |
|---|---|---|
| Developer | Novo Nordisk | Eli Lilly |
| Receptor Targets | GLP-1 | GLP-1 + GIP + Glucagon |
| Mechanism | Appetite suppression | Appetite suppression + liver fat oxidation |
| Average Weight Loss | 14.9% (68 weeks) | 24.2% (Phase 2, 48 weeks); 28.3% (Phase 3, 80 weeks) |
| Participants Losing 5%+ | 86.4% | 100% (Phase 2) |
| Participants Losing 15%+ | 50.5% | 83% (Phase 2) |
| Status | Approved (2021) | Five Phase 3 trials reported; U.S. submission planned Q1 2027 |
| Administration | Weekly subcutaneous injection | Weekly subcutaneous injection |
| Cardiovascular Data | SELECT trial: 20% MACE reduction | TRIUMPH-3 (adults with cardiovascular disease): 22.6% weight loss on 12 mg |
| Long-Term Safety Data | Extensive (5+ years) | Phase 3 trials up to 80 weeks |
| Current Availability | Widely available | Limited; see below |
| Insurance Coverage | Variable by plan | Not applicable |
| Type 2 Diabetes Indication | Yes (as Ozempic) | Being studied |
Side Effects Comparison
Both medications share similar gastrointestinal side effect profiles because they both activate GLP-1 receptors. However, there are important differences.
Semaglutide Side Effects (Well-Established)
Common (from STEP trial data):
- Nausea (44%)
- Diarrhea (30%)
- Vomiting (24%)
- Constipation (24%)
- Abdominal pain (20%)
- Headache (14%)
Serious but rare:
- Pancreatitis
- Gallbladder events (increased with rapid weight loss)
- Thyroid C-cell tumors (boxed warning based on animal studies)
Most GI side effects are dose-dependent and improve with continued use. The STEP trials showed that symptoms were most pronounced during the 16-week titration period and diminished significantly once participants reached their maintenance dose (Wilding et al., 2021).
Retatrutide Side Effects (Preliminary Data)
Common (from Phase 2 data):
- Nausea (25-45% depending on dose)
- Diarrhea (20-35%)
- Vomiting (10-20%)
- Constipation (10-15%)
- Decreased appetite
Notable differences:
- Dose-dependent increases in resting heart rate, which peaked around week 24 and then declined
- The glucagon receptor component may introduce metabolic effects not seen with GLP-1-only medications
- In Phase 3 TRIUMPH-1, 11.3% of participants on 12 mg stopped because of side effects, vs. 4.9% on placebo
The overall tolerability of retatrutide in the Phase 2 trial was described as acceptable, with most adverse events being mild to moderate. Proper dose titration was key to minimizing side effects (Jastreboff et al., 2023).
Muscle Preservation: A Critical Consideration
One concern with any rapid weight loss medication is the loss of lean muscle mass alongside fat. This is clinically important because muscle loss can reduce metabolic rate, impair functional capacity, and worsen long-term outcomes.
Semaglutide and Body Composition
Data from the STEP trials indicates that approximately 38–39% of weight lost with semaglutide came from lean mass, with the remainder from fat mass, in the STEP 1 DEXA sub-study published with the main trial in The New England Journal of Medicine (Wilding et al., 2021). While this lean mass loss is proportional to the total weight loss and generally considered acceptable, it underscores the importance of resistance training and adequate protein intake during treatment. Patients with low testosterone may face an even greater risk of muscle loss and should have hormone levels evaluated before starting treatment.
Retatrutide and Body Composition
Lilly’s DEXA sub-study of the Phase 2 type 2 diabetes trial found that total fat mass fell 23.2% on 12 mg and 26.1% on 8 mg at 36 weeks, and the researchers reported that the share of weight lost as lean mass was similar to other obesity treatments (Coskun et al., Lancet Diabetes & Endocrinology, 2025). In the obesity trial’s MRI sub-study, fat around the organs fell by up to 48% at 48 weeks (Sanyal et al., 2024).
Regardless of which medication is used, structured medical weight loss programs that include resistance training at least two to three times per week and protein intake of 1.2 to 1.6 grams per kilogram of body weight per day are essential to minimize muscle loss during pharmacologically assisted weight loss.
Availability and Access
Semaglutide
Semaglutide is widely available by prescription in the United States and internationally. As of 2026:
- Branded options (Wegovy, Ozempic) are available through most pharmacies
- Compounded semaglutide is available through licensed compounding pharmacies
- Insurance coverage varies significantly by plan; many plans now cover Wegovy for weight management
- Out-of-pocket costs range from approximately $200-500 per month (compounded) to $800-1,300+ per month (branded without insurance)
Retatrutide
Retatrutide is not yet sold as a branded prescription medicine. Patients encounter it through:
- Clinical trial participation in Eli Lilly studies
- Lilly’s expanded access program for adults with severe obesity-related complications
- Medical providers who can review the data with you
- Research chemical vendors (not recommended; quality and safety concerns)
We go through that access question in detail in how to get retatrutide.
Who Is Each Medication Best For?

Semaglutide May Be Best For:
- Individuals who want a well-studied medication with extensive long-term safety data
- Patients who prioritize cardiovascular risk reduction (supported by the SELECT trial)
- People seeking a medication with established insurance coverage pathways
- Individuals with moderate weight loss goals (10-15% of body weight)
- Patients who value the reassurance of a medication used by millions of people worldwide
Retatrutide May Be Best For:
- Individuals who need greater than 15-20% body weight loss
- People with significant metabolic dysfunction who may benefit from the glucagon receptor’s effects on liver fat
- Individuals with MASH (metabolic dysfunction-associated steatohepatitis) given the glucagon receptor’s role in hepatic fat metabolism
- Patients willing to use a newer medication with less long-term safety data in exchange for potentially greater efficacy
What to Expect During Treatment
Starting Semaglutide
- Weeks 1-4: Starting dose of 0.25 mg weekly; minimal weight loss expected; some GI adjustment
- Weeks 5-16: Gradual dose escalation every 4 weeks; increasing appetite suppression and weight loss; GI side effects most common during this phase
- Months 4-12: Maintenance dose reached; most significant weight loss occurs; symptoms typically stabilize
- Beyond 12 months: Continued weight maintenance with ongoing use; the STEP 5 trial showed sustained 15.2% weight loss at 2 years
Starting Retatrutide (Based on Clinical Trial Protocols)
- Weeks 1-4: Starting dose of 2 mg weekly; body adjustment period
- Weeks 5-12: Dose escalation about every 4 weeks toward the target dose (up to 12 mg); progressive increase in appetite suppression
- Weeks 12-48: Maintenance dose; average loss reached 17.4% by week 24 and 24.2% by week 48 on 12 mg in Phase 2
- Weeks 48-80: In Phase 3 TRIUMPH-1, weight loss on 12 mg continued to an average of 28.3% at 80 weeks
Personalized Treatment at Rewind Anti-Aging
Choosing the right weight loss medication is not a one-size-fits-all decision. At Rewind Anti-Aging of Miami, we take a personalized approach that considers your complete health profile, weight loss goals, medical history, and individual response to treatment.
Our comprehensive weight loss programs include:
- Medical evaluation and metabolic assessment to identify the best treatment approach
- Personalized medication selection with semaglutide, tirzepatide, and other evidence-based options
- Structured dose titration designed to maximize results while minimizing side effects
- Regular monitoring with bloodwork, body composition tracking, and clinical check-ins
- Nutrition and exercise guidance to optimize body composition and preserve lean mass
- Transition planning as new treatments like retatrutide become available
Whether semaglutide, tirzepatide, or eventually retatrutide is the right fit for your goals, our team provides the medical expertise and ongoing support needed for lasting results. Book a consultation with Rewind Anti-Aging to discuss which treatment approach is right for you.
Related Articles
- Retatrutide vs Tirzepatide: Which Peptide Is Better?
- How Does Retatrutide Work? The Triple-Action Peptide Explained
- Difference Between Tirzepatide and Semaglutide
References
- Jastreboff AM, Kaplan LM, Frías JP, et al. Triple-hormone-receptor agonist retatrutide for obesity — a Phase 2 trial. N Engl J Med. 2023;389(6):514-526. PubMed
- Wilding JPH, Batterham RL, Calanna S, et al. Once-weekly semaglutide in adults with overweight or obesity. N Engl J Med. 2021;384(11):989-1002. PubMed
- Lincoff AM, Brown-Frandsen K, Colhoun HM, et al. Semaglutide and cardiovascular outcomes in obesity without diabetes (SELECT). N Engl J Med. 2023;389(24):2221-2232. PubMed
- Blundell J, Finlayson G, Axelsen M, et al. Effects of once-weekly semaglutide on appetite, energy intake, control of eating, food preference, and body weight in subjects with obesity. Diabetes Obes Metab. 2017;19(9):1242-1251. PubMed
- Campbell JE, Drucker DJ. Pharmacology, physiology, and mechanisms of incretin hormone action. Cell Metab. 2013;17(6):819-837. PubMed
- Pocai A. Action and therapeutic potential of oxyntomodulin. Mol Metab. 2014;3(3):241-251. PubMed
- Wadden TA, Bailey TS, Billings LK, et al. Effect of subcutaneous semaglutide vs placebo as an adjunct to intensive behavioral therapy on body weight (STEP 3). JAMA. 2021;325(14):1403-1413. PubMed
- Garvey WT, Batterham RL, Bhatta M, et al. Two-year effects of semaglutide in adults with overweight or obesity (STEP 5). Nat Med. 2022;28(10):2083-2091. PubMed
- Sanyal AJ, et al. Triple hormone receptor agonist retatrutide for metabolic dysfunction-associated steatotic liver disease: a randomized phase 2a trial. Nat Med. 2024;30(7):2037. PMC
- Coskun T, Wu Q, Schloot NC, et al. Effects of retatrutide on body composition in people with type 2 diabetes. Lancet Diabetes Endocrinol. 2025;13(8):674. PubMed
- Coskun T, et al. LY3437943, a novel triple glucagon, GIP, and GLP-1 receptor agonist for glycemic control and weight loss. Cell Metab. 2022;34(9):1234. PubMed
Ready to explore your weight loss options? Rewind Anti-Aging of Miami offers personalized semaglutide therapy and other advanced treatments with comprehensive monitoring and support. Schedule a consultation →
This article is for informational purposes only and does not constitute medical advice. Always consult with a qualified healthcare provider before starting any weight loss treatment.
Frequently Asked Questions
Is retatrutide better than semaglutide for weight loss?
In their separate trials, retatrutide produced 24.2 percent average weight loss in 48 weeks (Phase 2) and 28.3 percent in 80 weeks (Phase 3 TRIUMPH-1) on 12 mg, compared with 14.9 percent in 68 weeks for semaglutide 2.4 mg in STEP 1. Semaglutide has more years of real-world use and cardiovascular outcome data from the SELECT trial.
What is the difference between a GLP-1 agonist and a triple agonist?
A GLP-1 agonist like semaglutide activates one receptor to suppress appetite and improve blood sugar. A triple agonist like retatrutide activates three receptors -- GLP-1, GIP, and glucagon -- addressing appetite, nutrient processing, and fat breakdown simultaneously.
Does retatrutide increase metabolism?
In animal studies, the glucagon receptor arm of retatrutide added calorie burn on top of reduced food intake. In people, the clearest effect is in the liver: a blood marker of fat burning rose two- to threefold, and liver fat fell 82 percent in 24 weeks on 12 mg in a Phase 2 substudy.
Does retatrutide cause muscle loss?
As with any large weight loss, some of the weight lost is lean mass. In Lilly's DEXA substudy in people with type 2 diabetes, fat mass fell 23 percent on 12 mg at 36 weeks, and the share of weight lost as lean mass was similar to other obesity treatments. Resistance training and adequate protein intake help preserve lean mass during weight loss.
Can I switch from semaglutide to retatrutide?
Transitioning from semaglutide to retatrutide is a clinical decision made with your provider. Both medications work through GLP-1 pathways, so the switch follows a structured titration plan.
How quickly does semaglutide work?
Most individuals notice reduced appetite within the first one to two weeks. Clinically meaningful weight loss, typically 5 percent or more of body weight, usually occurs within the first three to four months with continued use and lifestyle modifications.
More in weight loss
GLP-1 Pill Options in 2026: Oral Wegovy vs Foundayo
Two GLP-1 pill options reached US pharmacies in 2026: oral semaglutide and orforglipron. How they differ, what the trials showed, and who each one suits.
weight lossGLP-1 Microdosing: What a Lower Dose Actually Does
GLP-1 microdosing means staying below the standard maintenance dose on purpose. What the dose-response data support, what it does not, and who it suits.
weight lossTirzepatide Weight Loss in Miami: Who It Suits and How It Works
Tirzepatide weight loss in Miami: how the weekly GLP-1 and GIP medication works, what the trials show, who it suits, how the dose builds, and what monthly care involves.
⚕ Medical Disclaimer
The information on this page is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. All treatments at Rewind Anti-Aging of Miami are performed under the supervision of licensed medical professionals. Individual results may vary. Consult your physician before beginning any new treatment protocol.
Meet our clinical team →Not sure which treatment is right for you?
Take our free 2-minute assessment and get a personalized recommendation.
Areas We Serve in Miami & South Florida
Our clinic at 24 NW 29th Street is in Wynwood & Midtown, minutes from Edgewater and Brickell. We also care for patients across Coral Gables, Aventura, Key Biscayne, and Doral — plus the entire state of Florida via telehealth.
Take the Next Step
Our team at Rewind Anti-Aging in Miami is here to help you determine if semaglutide is right for your goals.